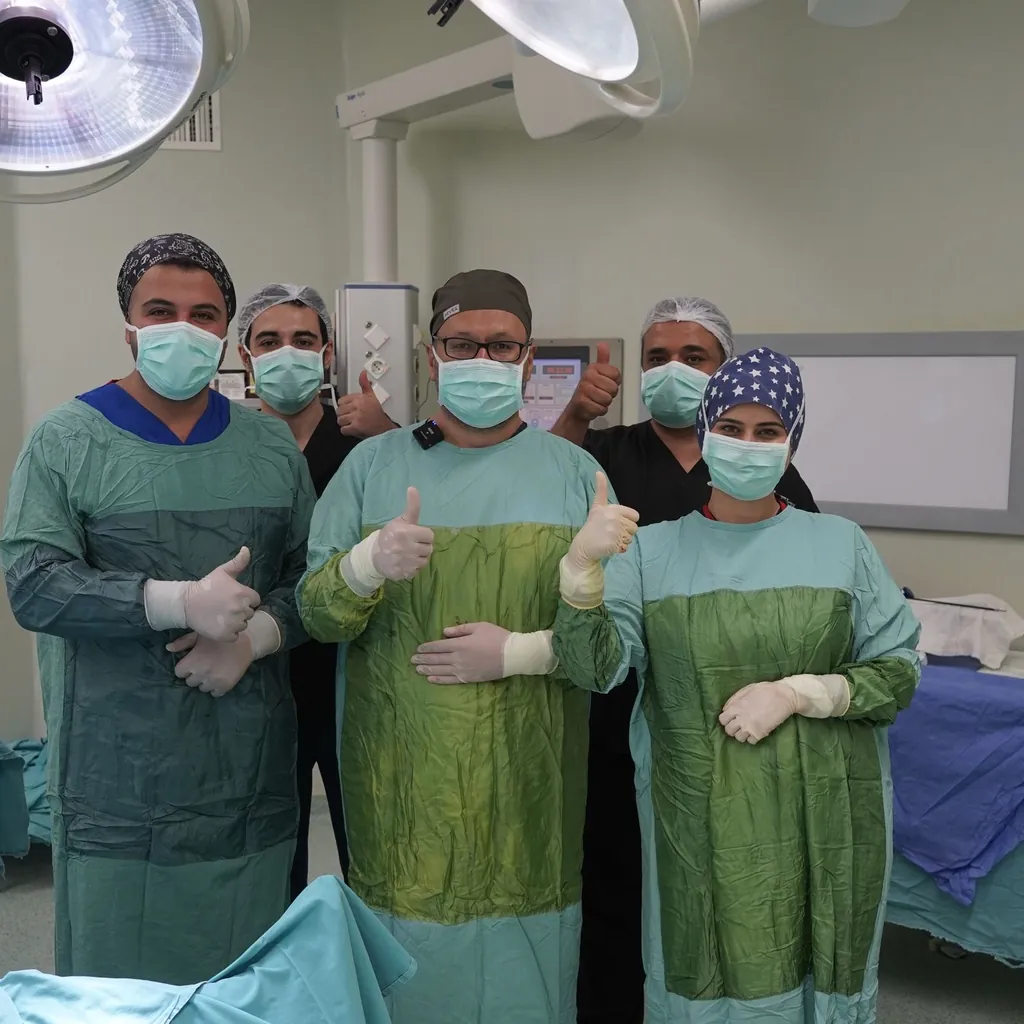
A team of five surgical staff in the operating room, including a woman, gives a thumbs-up.

Gynecological surgery

Surgery, step by step

Dr Gatri performs gynecological surgery and obstetrics at the Clinique de la Muette (Paris 16th), a five-minute walk from the practice.

Updated on 19 November 2026

The pathway

From consultation to the operating room

At the reception desk, a smiling patient talks with a receptionist in blue scrubs holding a tablet.
  1. Prior consultation at the practice — Dr Gatri explains the planned procedure, its expected benefits, its risks and the possible alternatives.
  2. Documents — you receive by e-mail an information sheet, an informed consent form and a detailed quotation, to be read carefully.
  3. Electronic signature — once all your questions have been answered, you accept the documents by electronic signature. No booking is made before your signature is received.
  4. Operating-room booking — the date is set at the clinic. This booking reserves an operating room, an anesthetist and, if the procedure requires it, a surgical assistant — resources set aside specifically for you. An anesthesia consultation is scheduled at the clinic before the operation.
  5. Procedure and follow-up — day surgery or short stay depending on the procedure, then a postoperative consultation at the practice.
Punctuality and cancellation. Because the booking reserves an operating room, an anesthetist and sometimes a surgical assistant for you, it is essential to arrive on time on the day of the procedure. A cancellation is always difficult to reorganize; cancelling two or three days before the date is particularly damaging, as these resources can no longer be reallocated to another patient. Please inform the practice as early as possible if you are unable to attend.
Clinic charges. The practice's quotation covers Dr Gatri's fees only. Clinic charges (stay, operating room, equipment) and the anesthetist's fees are arranged directly with the clinic — details under practical information.

Book an appointment — Dr Gatri

Procedures

The procedures explained

Simplified diagrams, for general information. After your consultation, you receive by e-mail detailed information tailored to your situation, an informed-consent form and a quotation, to be accepted by electronic signature.

Uterus

Dedicated page: Uterine fibroids

Operative hysteroscopy

Treatment of the inside of the uterus through the natural passages, with no incision: a tube fitted with an optical system is introduced through the cervical canal. It makes it possible to remove polyps or fibroids located in the uterine cavity, and to treat septa or synechiae (adhesions). Diagnostic hysteroscopy is performed at the practice; the operative form takes place at the clinic, under general anesthesia, as day surgery (you go home the same day). It takes about 45 minutes.

Information sheet · Operative hysteroscopy — through the natural passages PDF Clinique de la Muette · diagnostic hysteroscopy at the practice
Operative hysteroscopy: the tube fitted with an optical system passes through the cervical canal (diagram, front view).
  1. Tube fitted with an optical system, through the cervical canal
  2. Fluid distends the uterus
  3. Ovary
  4. Vagina
  5. Polyp (or fibroid) in the uterine cavity
  6. Instruments, including electrical ones
  7. Lining
  8. Uterus
  9. Cervix
  10. Fallopian tube
Diagram Wagram Clinic, 2026.

Myomectomy

Removal of one or more fibroids while keeping the uterus. You therefore keep your periods and, possibly, the possibility of a future pregnancy. Depending on the size, number and location of the fibroids, it is performed by hysteroscopy, laparoscopy or open surgery. The chosen technique is explained during your consultation. The scar left on the uterus may be an area of weakness and, in some cases, require delivery by cesarean (caesarean) section. It is advisable to allow a healing interval between the procedure and any pregnancy.

Information sheet · Myomectomy — laparoscopy PDF Information sheet · Myomectomy — open surgery PDF (laparotomy) Clinique de la Muette
See the diagram
Myomectomy: opening the wall of the uterus, removing the fibroid, closing the wall (diagram, front view). 1 — Wall opened: the surgeon opens the wall of the uterus. 2 — Fibroid removed, taken out in small pieces. 3 — Wall closed: the uterus is kept. In purple: the fibroid (myoma). In blue-green: the wall opened, then closed. In blue-green, outlined with dots: the part removed during the operation. Front view: the right of the image is the patient's left side. Diagram Wagram Clinic, 2026.

Hysterectomy

Removal of all or part of the uterus when conservative treatments are no longer sufficient (symptomatic fibroids, resistant bleeding, certain lesions). Three possible approaches — vaginal, laparoscopic or abdominal — chosen according to your situation.

Information sheet · Hysterectomy — vaginal approach PDF Information sheet · Hysterectomy — laparoscopy PDF Information sheet · Hysterectomy — open surgery PDF (laparotomy) Clinique de la Muette
See the diagram
The different types of hysterectomy: A, subtotal; B, total; C, with adnexectomy (diagram, front view). A — subtotal: the uterus is removed, the cervix is left in place. B — total: the body of the uterus and the cervix are removed. C — with adnexectomy: the ovaries and fallopian tubes, on one side or both. In blue-green, outlined with dots: the part removed during the operation. Front view: the right of the image is the patient's left side.
  1. Body of the uterus
  2. Fallopian tube
  3. Ovary
  4. Cervix
  5. Vagina
Diagram Wagram Clinic, 2026.
See the diagram
Endometrectomy: the endometrium, the lining of the inside of the uterus, is the part that is removed (diagram, front view).
  1. Cavity
  2. Ovary
  3. Myometrium
  4. Vagina
  5. Fallopian tube
  6. Endometrium: the lining of the inside of the uterus; this is what is removed
  7. Uterus
  8. Cervix
Diagram Wagram Clinic, 2026.

Endometrial ablation — second-generation techniques

Destruction of the uterine lining by heat (thermal destruction), by contact with a small balloon or another type of applicator placed in the uterus, without loop resection: a small camera first checks the cavity, then the device destroys the lining, to treat very heavy periods when medical treatment is not enough. A short procedure, most often as day surgery, for women with no further pregnancy plans: it reduces fertility, and contraception remains necessary after the procedure. According to the practice's information sheet, the effectiveness of thermal destruction, in reducing bleeding or lower abdominal pain, is around 50 to 80%. If it fails, your surgeon will offer you other solutions.

Information sheet · Second-generation endometrial ablation — through the natural passages PDF (thermal destruction) Clinique de la Muette

Cervix

Cervical conization

Removal of a cone-shaped fragment of the cervix to treat precancerous lesions identified during colposcopy. A procedure of about 30 minutes, under general anesthesia, as day surgery, followed by regular smear-test surveillance. It preserves the possibility of pregnancy; the risk of premature birth is slightly increased in later pregnancies: tell the professionals who will care for your future pregnancies about this conization.

Information sheet · Cone biopsy — through the natural passages PDF (conisation) Clinique de la Muette
See the diagram
Cone biopsy (conisation), through the natural passages: the cone-shaped portion of the cervix that is removed (diagram, front view).
  1. Cervical canal
  2. Height: on average 15 mm
  3. Base: 1 to 2 cm
  4. Cervix
  5. Cone-shaped portion of the cervix
  6. Surface of the cervix
  7. Vagina
In blue-green, outlined with dots: the part removed during the operation. Front view: the right of the image is the patient's left side. Diagram Wagram Clinic, 2026.

Ovaries and tubes

Dedicated page: Ovarian cysts

See the diagram
Ovarian cystectomy (diagram, front view).
  1. Ovarian cystectomy: removal of the cyst, keeping the ovary.
  2. Light dots: the adnexa (ovary and tube). Once started, the operation may have to be extended to removal of the adnexa.
  3. Uterus
  4. Fallopian tube
  5. Ovary
Diagram Wagram Clinic, 2026.

Ovarian cysts · adnexectomy

Removal of an ovarian cyst, an ovary (oophorectomy) or a fallopian tube (salpingectomy), most often by laparoscopy — a small incision, usually at the navel, and two or three others of 5 to 12 mm — with a quick recovery.

Information sheet · Ovarian cystectomy — laparoscopy PDF Information sheet · Adnexectomy — laparoscopy PDF Information sheet · Salpingectomy — laparoscopy PDF Clinique de la Muette

Adnexectomy by the vaginal route (vNOTES)

Removal of the ovary and tube through the natural passages, endoscopically assisted: there is no scar on the abdomen, and pain after the operation is generally mild. The technique is offered when the anatomy and indication allow.

Information sheet · Ovarian cystectomy — vaginal approach PDF (vNOTES) Information sheet · Adnexectomy — vaginal approach PDF (vNOTES) Information sheet · Salpingectomy — vaginal approach PDF (vNOTES) Clinique de la Muette
See the diagram
The vaginal route (vNOTES technique): through the natural passages, with no incision of the skin (diagram, side view).
  1. Uterus
  2. Vagina
  3. It is performed by the vaginal route, using the vNOTES technique (short for vaginal natural orifice transluminal endoscopic surgery): the operation is carried out through the natural passages, with no incision of the skin.
Diagram Wagram Clinic, 2026.
See the diagram
Salpingectomy (diagram, front view).
  1. Total salpingectomy: complete removal of the fallopian tube, keeping the ovary.
  2. After a salpingectomy, the ovaries stay in place.
  3. Uterus
  4. Permanent contraception: removal of both fallopian tubes.
Diagram Wagram Clinic, 2026.

Tubal ligation

A permanent sterilization method, regulated by French law: a four-month reflection period after the first consultation, then written confirmation. Three possible approaches — by laparoscopy, by the vaginal route (vNOTES technique) or by open surgery (laparotomy). Full information is provided during your consultation.

Information sheet · Tubal sterilisation — open surgery PDF (laparotomy) Information sheet · Tubal sterilisation — vaginal approach PDF (vNOTES) Information sheet · Tubal sterilisation — laparoscopy PDF Clinique de la Muette

Endometriosis

Dedicated page: Endometriosis

Endometriosis surgery

The operation consists of destroying and/or removing the endometriosis lesions located outside the uterus; it is most often performed by laparoscopy, after complete imaging assessment. The indication is decided together with you, according to pain and any pregnancy plans.

Information sheet · Endometriosis surgery — laparoscopy PDF Information sheet · Understanding endometriosisInformation sheet · Understanding endometriosis Clinique de la Muette
See the diagram
Endometriosis: lesions outside the uterus (diagram, side view).
  1. Ovary
  2. Ovary affected (endometrioma)
  3. Uterus
  4. Bladder
  5. Colon
  6. Deep disease: rectum
  7. Rectum
  8. Rectovaginal septum
  9. Vagina
  10. Cervix
Diagram Wagram Clinic, 2026.

Pelvic floor

Dedicated page: Incontinence & prolapse

Prolapse surgery

Repair of pelvic organ prolapse (bladder, uterus, rectum), vaginally or by laparoscopic sacrocolpopexy. The choice of technique depends on the organ concerned, your age and your lifestyle.

Sacrospinous fixation — through the vagina: the top of the vagina is suspended with stitches to a deep ligament of the pelvis, the sacrospinous ligament. It uses only your own tissues, without an implant. Information sheet · Sacrospinous fixation — vaginal approach PDF Colpocleisis, or the Lefort procedure — through the vagina, which is closed. It uses only your own tissues, without an implant. It may be offered to elderly patients for whom anesthesia carries a significant risk, and who are no longer sexually active. Information sheet · Colpocleisis — vaginal approach PDF (Lefort procedure) Information sheet · Anterior and posterior vaginal repair PDF (colpoperineorrhaphy) Sacrocolpopexy — by laparoscopy (keyhole surgery), through small incisions in the abdomen: it puts the organs back in place and reinforces their support with a synthetic implant (a “mesh”), attached to a very strong ligament located in front of the spine, at the level of the promontory. Information sheet · Prolapse repair by sacrocolpopexy — laparoscopy PDF Clinique de la Muette
See the diagram
Cystocele, rectocele and their repair (diagram, side view). A — Organ descent: cystocele (left), rectocele (right). B — The repair, with your own tissues, without mesh. In orange: the organ bulging into the wall of the vagina. In blue-green, outlined with dots: the operated area, the front wall and the back wall of the vagina. Side view: the belly is on the left of the image, the back on the right.
  1. Uterus
  2. Bladder
  3. Cystocele
  4. Vagina
  5. Rectum
  6. Rectocele
  7. Perineum
  8. The wall of the vagina is opened
  9. Put back in place
  10. Put back in place
  11. Supporting tissues tightened, dissolvable stitches
Diagram Wagram Clinic, 2026.
See the diagram
The transobturator tape: placed under the urethra, it passes through the obturator foramen of the pelvis and comes out near the thigh creases (diagram, front view).
  1. Pelvis
  2. Bladder
  3. Obturator foramen
  4. Vagina
  5. Tape: under the urethra, tension-free, like a hammock
  6. Urethra
  7. Pubis
  8. Passes through the obturator foramen, comes out near the thigh creases
Diagram Wagram Clinic, 2026.

Urinary incontinence surgery

Placement, under the urethra, of a synthetic, non-dissolvable sling made of polypropylene, to treat stress urinary incontinence when rehabilitation is not sufficient. A procedure of about 30 minutes, as day surgery.

Information sheet · Surgery for stress urinary incontinence — transobturator tape PDF Information sheet · Surgery for stress urinary incontinence — retropubic tape PDF Clinique de la Muette

Other procedures

Procedures performed at the Clinique de la Muette.

Adnexectomy (salpingo-oophorectomy)

Removal of an ovary and the fallopian tube on the same side.

Suction curettage of the uterine cavity

An operation that empties the contents of the uterine cavity, or that takes a sample of its lining for analysis. It is carried out through the natural passages, without any incision, at the Clinique de la Muette, under general anesthesia; it takes about 30 minutes, and you go home a few hours later. It is offered after a missed miscarriage in the first trimester or a miscarriage, to empty the uterus; in the case of tissue remaining after a pregnancy; or to analyze (analyse) the lining of the uterus.

Information sheet · Suction curettage of the uterine cavity PDF
See the diagram
Suction: a thin cannula in the uterine cavity (diagram, side view).
  1. Uterus
  2. Bladder
  3. Vagina
  4. Thin cannula
  5. To suction
  6. Tip of the cannula
  7. Cervix
  8. Rectum
Diagram Wagram Clinic, 2026.
Laparotomy

Open abdominal surgery, reserved for emergencies or complex conditions.

The open surgery (laparotomy) sheets for myomectomy, hysterectomy and tubal sterilization are with those procedures, further up this page.

Information sheet · Ovarian cystectomy — open surgery PDF (laparotomy) Information sheet · Adnexectomy — open surgery PDF (laparotomy) Information sheet · Salpingectomy — open surgery PDF (laparotomy) Information sheet · Endometriosis surgery — open surgery PDF (laparotomy)
Vaginal tear repair
See the diagram
Vaginal tear repair (diagram, front view).
  1. Clitoris
  2. Labia minora
  3. Labia majora
  4. Fissure of the posterior fourchette
  5. Urethral opening
  6. Entrance to the vagina
  7. Anus
In purple: the fissure, a small split in the skin at the bottom of the entrance to the vagina. Front view: the right of the image is the patient's left side. Diagram Wagram Clinic, 2026.

Surgical repair of vaginal tears or lesions.

Intimate surgery

Intimate surgery

Dr Gatri has an established practice in vulvar and perineal surgery. These procedures address functional discomfort; they are explained fully and without judgment.

Intimate surgery →

Information

Risks and complications: what to know before deciding

Every operation carries risks; Dr Gatri goes through them with you at the consultation and gives you the practice's information sheet for the procedure planned. The points below are common to gynecological surgery; each sheet sets out its own.

  • Common and not serious — after a laparoscopy, the practice's information sheets describe the possible side effects of anesthesia (anaesthesia) — nausea, vomiting, drowsiness — and pain, mainly in the abdomen, that may spread to the shoulders, caused by the gas introduced into the abdomen; modern pain management tends to reduce it. A hematoma (haematoma) or an infection (abscess) may occur at the incision, usually needing only simple local care. Recovery after a hysteroscopy is almost painless and straightforward in the majority of cases, and conization causes no pain after the operation, possibly some passing discomfort similar to painful periods. After a myomectomy, the practice's information sheet states that the first 48 hours are often painful and require strong painkillers, and that a usually mild urinary infection is not uncommon.
  • Rare — perforation of the uterus may occur during a hysteroscopy and prevent completion of the planned procedure. After a conization, the main risk is bleeding: the practice's information sheet states that it may occur from the first hours and during the 15 days following the operation. The risk of phlebitis and pulmonary embolism is exceptional after a laparoscopy. Very exceptionally, serious injury to the internal organs of the abdomen — bowel, blood vessels, urinary tract — may occur and require opening of the abdomen and, in some cases, a blood transfusion. During a hysterectomy or a myomectomy, life-threatening bleeding exceptionally calls for a transfusion of blood or blood products. As with any surgery, these operations may very exceptionally involve a life-threatening risk or serious after-effects.
  • What increases them — the practice's information sheets say so: certain risks may be increased by your condition, your medical history or by treatment taken before the operation. It is essential to tell the doctor about your personal and family history, about all the treatments and medicines you take, and about any allergies. The practice's information sheets add that smoking increases the risk of surgical complications of any operation, and state that stopping smoking six to eight weeks before the procedure removes this additional risk.
  • Warning signs — when to call — once home, the hysterectomy sheets list the symptoms that should prompt you to seek advice: burning or frequent urination, which may be due to a urinary infection: see your general practitioner for a urine test; abnormal or foul-smelling vaginal bleeding, or a high temperature, which may be a sign of an infection or an infected hematoma: consult your surgeon; nausea and vomiting with fever: consult your surgeon; a red and painful scar. Calf pain or difficulty breathing: call your general practitioner promptly, to rule out phlebitis. After a conization, continuous bleeding should prompt you to seek advice as soon as possible. After a curettage: if a fever above 38 °C, very heavy blood loss (a night-time sanitary pad changed every 30 minutes for 2 hours), severe lower abdominal pain, feeling faint or any other abnormality appears, you must inform your doctor without delay.
  • The sheet you are given — each procedure has its own, handed to you and talked through at the consultation: Information sheet · Ovarian cystectomy — laparoscopy PDF Information sheet · Adnexectomy — laparoscopy PDF Information sheet · Salpingectomy — laparoscopy PDF Information sheet · Tubal sterilisation — laparoscopy PDF Information sheet · Endometriosis surgery — laparoscopy PDF Information sheet · Operative hysteroscopy — through the natural passages PDF Information sheet · Myomectomy — laparoscopy PDF Information sheet · Myomectomy — open surgery PDF (laparotomy) Information sheet · Hysterectomy — vaginal approach PDF Information sheet · Hysterectomy — laparoscopy PDF Information sheet · Hysterectomy — open surgery PDF (laparotomy) Information sheet · Cone biopsy — through the natural passages PDF (conisation)

Procedure by procedure

Hospital stay, anesthesia and recovery

For each procedure, in the order of the fee schedule: the length of the hospital stay, the length of the procedure, the anesthesia and the timing of the check-up consultation at the practice; for some procedures, fasting and the precautions for recovery. Dr Gatri tells you at the consultation what is planned in your case.

Surgery at the clinic

ProcedureHospital stayLength of the procedureAnesthesiaCheck-up consultationFastingPrecautions
Vaginal delivery3 days after the birth—Regional2 to 3 weeks after——
Cesarean section4 days after the cesareanabout 45 min to 1 hourRegional3 to 4 weeks after8 hoursBaths resume after 3 weeks, intercourse once the bleeding has stopped.
ConizationDay surgery: you go home the same dayabout 30 minGeneral3 to 4 weeks after12 hoursBaths, the swimming pool and intercourse resume after 4 to 6 weeks; no long journeys or strenuous sport for the following 20 days.
Operative hysteroscopyDay surgery: you go home the same dayabout 45 minGeneral3 to 4 weeks after—No tampons or menstrual cup; physical and sexual activity resume as soon as the bleeding stops.
CurettageDay surgery: you go home the same dayabout 30 minGeneral3 to 4 weeks after—For about two weeks, and as long as there is any blood loss: no baths, water activities, tampons or menstrual cups, and no intercourse.
Myomectomy — laparoscopy2 to 3 daysabout 1½ to 2 hoursGeneral3 to 4 weeks after—Baths resume after at least 15 days, sexual activity after the check-up consultation.
Myomectomy — laparotomy2 to 3 daysabout 1 to 1½ hoursGeneral3 to 4 weeks after—Baths resume after at least 15 days, sexual activity after the check-up consultation.
Hysterectomy — laparoscopy1 to 2 daysabout 1½ to 2 hoursGeneral3 to 4 weeks after—No baths for 3 weeks; sanitary towels rather than tampons; intercourse 4 to 6 weeks after the procedure.
Hysterectomy — abdominal approach1 to 2 daysabout 1½ to 2 hoursGeneral3 to 4 weeks after—No baths for 3 weeks; sanitary towels rather than tampons; no heavy loads for a few weeks; intercourse 4 to 6 weeks after the procedure.
Hysterectomy — vaginal approach1 dayabout 1½ hoursGeneral3 to 4 weeks after—No baths for 3 weeks; sanitary towels rather than tampons; intercourse 4 to 6 weeks after the procedure.
Ovarian cystectomy — laparoscopy1 dayabout 1 hourGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Ovarian cystectomy — laparotomy1 dayabout 1½ hoursGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Adnexectomy — laparoscopyDay surgery: you go home the same dayabout 1½ hoursGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Adnexectomy — laparotomy1 dayabout 1½ hoursGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Salpingectomy — laparoscopyDay surgery: you go home the same dayabout 1 hourGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Salpingectomy — laparotomy1 dayabout 1½ hoursGeneral3 to 4 weeks after—Until the follow-up consultation: no baths, intercourse or loads of more than 5 kg.
Tubal ligation — laparoscopyDay surgery: you go home the same dayabout 1 hourGeneral3 to 4 weeks after—No baths or swimming for 15 days; intercourse resumes normally.
Endometriosis surgery — laparoscopy2 daysabout 2 hoursGeneral3 to 4 weeks after—Baths resume after a week.
Endometriosis surgery — laparotomy2 daysabout 2 hoursGeneral3 to 4 weeks after—Baths resume after a week.
Prolapse repair — sacrocolpopexy2 daysabout 3 hoursGeneral3 to 4 weeks after—No penetrative sex for 4 weeks, and no tampons or baths for about six weeks; for the first few weeks, no exertion, sport or heavy lifting; no strenuous effort for two months.
Vaginal tightening — functional version (colpoperineorrhaphy)Day surgery: you go home the same dayabout 2½ hoursGeneral3 to 4 weeks after—Baths, the swimming pool and intercourse resume after 4 to 6 weeks; no exertion, sport or heavy lifting for about six weeks; no strenuous effort for two months.
Incontinence surgery — transobturator slingDay surgery: you go home the same dayabout 30 minGeneral3 to 4 weeks after—For about two weeks, no strenuous effort, loads of more than 5 kg or baths; for a month, no penetrative intercourse or tampons; sport stopped for 1 to 2 months.
Incontinence surgery — retropubic slingDay surgery: you go home the same dayabout 30 minGeneral3 to 4 weeks after—For about two weeks, no strenuous effort, loads of more than 5 kg or baths; for a month, no penetrative intercourse or tampons; sport stopped for 1 to 2 months.
Labiaplasty — functional versionDay surgery: you go home the same dayabout 1 hourGeneral3 to 4 weeks after—Baths, the swimming pool and intercourse resume after 4 to 6 weeks; tampons and any strenuous sporting activity, after the follow-up consultation.
Clitoral hood reduction — functional versionDay surgery: you go home the same dayabout 1 hourGeneral4 weeks after—Intercourse, baths and the swimming pool resume after 4 to 6 weeks; tampons and strenuous sport, after 4 weeks.
Hymenoplasty — therapeutic versionDay surgery: you go home the same dayabout 1 hourGeneral3 to 4 weeks after—No intercourse after the procedure; until the follow-up consultation, no tampons, baths, swimming pools or strenuous sport.

Laser surgery, at the practice

ProcedureHospital stayLength of the procedureAnesthesiaCheck-up consultationFastingPrecautions
Laser labiaplasty — functional versionNo hospital stay: you go home the same dayabout 45 minLocal15 days afterYou eat normallyBaths, the swimming pool and intercourse resume after 15 days.
Laser clitoral hood reduction — functional versionNo hospital stay: you go home the same dayabout 30 minLocal15 days afterYou eat normallyBaths, the swimming pool and intercourse resume after 15 days.

Durations and arrangements as given by Dr Gatri.

Frequently asked questions

Your questions, our answers

Will I have surgery on the day of the consultation?

The consultation for surgery is an appointment at the practice. Dr Gatri examines your situation, explains the planned procedure and answers your questions. If the procedure is decided on, you receive a quotation and an informed-consent form; once they are signed, a date is set for the procedure — at the Clinique de la Muette for surgery, at the practice for laser.

How do I prepare for surgery?

It all starts with the consultation at the practice: Dr Gatri explains the planned procedure, its expected benefits, its risks and the alternatives. You then receive by e-mail an information sheet, an informed-consent form and a detailed quotation, to be accepted by electronic signature. An anesthesia consultation takes place at the clinic beforehand. The practice's information sheets state that stopping smoking six to eight weeks ahead of surgery removes the added risk of complications linked to tobacco.

What kind of anesthetic (anaesthetic) will I have?

It depends on the procedure, and the anesthetist (anaesthetist) settles it with you at the anesthesia consultation held at the clinic. Dr Gatri indicates a general anesthetic for gynecologic surgery and intimate surgery at the clinic — the practice's information sheets also provide, depending on the case, for regional anesthesia for the vaginal approach (vNOTES), sacrospinous fixation, colpocleisis and vulvoperineoplasty, and for regional or local anesthesia for second-generation endometrial ablation — a regional anesthetic for vaginal delivery and cesarean section, and a local anesthetic for laser labiaplasty and laser clitoral hood reduction, at the practice; the Hospital stay, anesthesia and recovery table gives it for each procedure. A gynecologic (gynaecologic) examination is carried out under anesthetic, immediately before the procedure.

Day surgery or a hospital stay?

It depends on the procedure. The length of the hospital stay is given, procedure by procedure, in the Hospital stay, anesthesia and recovery table. Dr Gatri tells you at the consultation what is planned in your case.

Will it hurt afterwards?

Pain relief is prescribed as a matter of course. The practice's information sheets describe recovery that is almost painless and straightforward in the majority of cases after hysteroscopy; no pain after conization, possibly some passing discomfort similar to painful periods; and abdominal pain that may spread to the shoulders after laparoscopy, caused by the gas used during the operation. After a myomectomy, the first forty-eight hours are often painful and call for strong painkillers.

When can I go back to work, to sport and to sex?

It depends on the procedure and on the work you do. The practice's information sheets give a convalescence rarely exceeding fifteen days after vaginal or laparoscopic hysterectomy, and a return to work or sport that may take four to six weeks after abdominal hysterectomy; after conization, four to six weeks with no baths, no swimming pools and no sexual intercourse, and twenty days without long journeys or strenuous sport; after hysteroscopy, physical and sexual activity resumes as soon as the bleeding stops. Your sick leave is written at the consultation, to suit your situation.

Will I have a scar?

That depends on the surgical route. Hysteroscopy and conization go through the natural passages, with no incision; adnexectomy by the vaginal route (vNOTES) goes through the vagina and leaves the abdomen intact. Laparoscopy leaves a small incision, most often at the navel, and two or three other incisions of 5 to 12 mm in the lower abdomen. The practice's information sheet states that, with the abdominal route, the scar is most often about ten centimeters (centimetres) long and lies horizontally above the pubis; the wound is usually closed with stitches, most of the time dissolvable, or with staples, removed after eight to ten days.

What do I sign, and what if I change my mind?

After the consultation you receive by e-mail an information sheet, an informed-consent form and a detailed quotation, to read and then accept by electronic signature; the practice's information sheet for your procedure is handed to you. No booking is made at the clinic before your signature is received. Your consent remains yours: you withdraw it whenever you decide to, and telling the practice early lets the reserved operating room go to another patient.

Is it covered by health insurance?

In part. Consultations, tests and procedures listed in the French national schedule are partly covered by the French health insurance (Assurance maladie). The practice applies direct billing to the French national health insurance (tiers payant): with an up-to-date carte Vitale, you do not pay that part upfront. What remains payable by you includes the excess fee (dépassement d'honoraires), which may be reimbursed by your complementary insurer (mutuelle), depending on your policy. Clinic charges and the anesthetist's fees are arranged directly with the Clinique de la Muette. The full picture is in “Fees and reimbursement”, further down.

Fees

Fees and reimbursement

Consultations, tests and procedures listed in the French national schedule are partly covered by the French health insurance (Assurance maladie). The practice applies direct billing to the French national health insurance (tiers payant): with an up-to-date carte Vitale, you do not pay that part upfront. What remains payable by you includes the excess fee (dépassement d'honoraires), which may be reimbursed by your complementary insurer (mutuelle), depending on your policy. The practice's quotation details Dr Gatri's fees, distinguishing the part paid by the Assurance maladie from the excess fee (dépassement d'honoraires), and is provided before any procedure; clinic charges and the anesthetist's fees are arranged directly with the Clinique de la Muette. Fees are listed in the fee schedule and displayed at the practice. The information framework of this site is described on the Patient information and ethics page.

Consultation for surgery: €120 to €160. This consultation takes place at the practice: Dr Gatri examines your situation and explains the options. If a procedure is decided on, you receive a quotation and an informed-consent form to sign; a date is then set for the procedure at the clinic. All fees and the framework: Fees.

Appointments

Book an appointment

Appointments can be booked online via Doctolib or by telephone through the secretariat: +33 1 40 72 00 55.

Doctolib — Dr Chaima Gatri